
Data-Driven Cold Calling for Healthcare Sales
Pre-call research using provider data turns generic cold calls into relevant conversations. Here is the workflow.
Updated April 2026
Why Cold Calling in Healthcare Requires Better Data
Generic cold calls fail here. "Hi, I'm calling from [company], and we help healthcare organizations improve outcomes" will get you hung up on or routed to voicemail. The person on the other end has heard a version of that pitch dozens of times. They have no reason to stay on the line.
This guide walks through the complete pre-call research workflow, optimal call timing, data-informed opening lines, and gatekeeper strategies, written specifically for healthcare sales. The advice here applies whether you're selling medical devices, health IT, staffing services, or revenue cycle solutions.

The 5-Minute Pre-Call Research Workflow
Step 1: NPI lookup (30 seconds). Start with the NPI registry or your provider data platform. Confirm the provider's name, credential, specialty, and practice address. This prevents the embarrassing mistake of calling a pediatrician to pitch an orthopedic device. It also confirms you have the right location, many providers practice at multiple sites.
Step 2: Practice size and structure (60 seconds). How many providers work at this location? Is it a solo practice, a small group, or part of a large system? This determines who makes purchasing decisions. In a 3-physician practice, the senior partner decides. In a 50-provider group, there's an operations director or administrator. In a hospital-owned practice, decisions may be made at the system level. Provider data platforms aggregate this, saving you from manually counting names on a website.
Step 3: Technology detection (60 seconds). What EHR, practice management system, or relevant technology does the practice use? If you sell into EHR workflows, knowing they run Epic vs. Athenahealth changes your entire pitch. If you sell devices, knowing the existing equipment manufacturer tells you whether you're displacing a competitor or filling a gap. Commercial provider databases increasingly include technology install data.
Step 4: Decision-maker identification (90 seconds). Start with the role tied to the buying decision: practice administrator, office manager, department head, or medical director. Use a current business number when one is published, confirm the person's current employer, and record the source date before outreach.
Step 5: Trigger event scan (60 seconds). Has anything changed recently? New location opened, new physician joined, leadership change, merger announcement, or new construction. Check your data platform's update alerts, a quick Google News search, and the practice's own website. A trigger event gives you a reason to call beyond "I want to sell you something." It turns a cold call into a timely call.
Timing Your Calls: When Healthcare Contacts Answer
Day of the week matters. For physician practices, Monday is the busiest clinical day (weekend patient calls, catch-up appointments). Tuesday through Thursday are your best days. For hospitals, avoid calling the first week of the month (month-end close aftermath, new resident rotations in July). Wednesday and Thursday tend to outperform other days across most healthcare contacts.
Seasonal patterns. Healthcare has pronounced seasonality. January through March is budget season for many hospitals, good for budget-related conversations, bad for getting attention on new evaluations. Summer months (June-August) are slower for elective procedures, which means some physicians have more availability. Avoid the last two weeks of December entirely. Track your own connect rates by time slot and day to build a data set specific to your territory and buyer persona.
The timing windows above, condensed into one reference:
| Contact type | Best windows | Avoid |
|---|---|---|
| Surgeons | Verify the measured value and observation date before use. | Verify the measured value and observation date before use. |
| Primary care physicians | Verify the measured value and observation date before use. | Mid-morning and mid-afternoon clinic hours |
| Practice administrators | Verify the measured value and observation date before use. | Verify the measured value and observation date before use. |
| Hospital executives | Verify the measured value and observation date before use. | Friday afternoons, first week of the month |
The Data-Informed Opening: First 15 Seconds
The pattern: name, company, specific observation, question. Not "Hi Dr. Patel, I'm with MedTech Corp and we help practices like yours improve efficiency." Instead: "Hi Dr. Patel, I'm Alex from MedTech Corp. I noticed your group recently added a third orthopedic surgeon at your Westside location, are you seeing more demand for [specific procedure]?" The second version works because it references something specific and true about the practice. It signals you're not reading from a script.
What to reference, based on your pre-call data. Practice size changes (new providers added), technology (their current EHR or device), specialty-specific trends (tie your product to their clinical focus), organizational changes (new location, affiliation change), or publicly available metrics. The reference should be neutral or positive, don't open with "I see your patient satisfaction scores dropped." Use data to show you understand their world rather than to create anxiety.
For gatekeepers. When you reach a front desk or receptionist, the data-informed approach still applies; however, differently. Know the name of the person you're trying to reach (don't say "the person who handles purchasing"). Know their title. If asked "what is this regarding," have a specific, non-salesy answer: "I'm following up on the technology assessment Dr. Chen's team is running" or "I have information about [specific topic] that Dr. Chen's office manager requested we send over." This works only if it's truthful, fabricating a reason will backfire when the gatekeeper checks.
Multi-channel follow-up. A cold call alone rarely converts in healthcare. Plan to follow the call with an email that same day, referencing your voicemail and including one useful piece of information (not a product brochure). Provider data gives you the direct email addresses you need. The call-then-email sequence consistently outperforms either channel alone.
Handling Gatekeepers When You Know the Org Structure
Healthcare organizations have more gatekeeping layers than most industries. Physician practices have front desk staff. Hospitals have operators, administrative assistants, and department coordinators. Getting past these layers is a common challenge; however, having provider data gives you structural advantages most callers don't have.
Know the org chart before you call. When you know the practice administrator's name, the office manager's name, and the physicians' names, you can navigate the phone tree with confidence. "Hi, this is Sarah from DataMed, is Karen available? Karen Thompson, your practice administrator." That sounds different from "Can I speak to whoever handles your technology purchasing?" The first version suggests an existing relationship or at minimum, a prepared caller. The second is immediately flagged as a sales call.
Use direct dial numbers. The most effective gatekeeper strategy is to bypass them entirely. Commercial provider databases often include direct phone numbers for administrators and department heads, numbers that don't route through the main switchboard. If your data source provides direct dials, use them. Your connect rate will be materially higher than calling the main office line.
Use the multi-location angle. If the provider group has multiple locations, call a secondary or satellite office rather than the main location. Satellite offices tend to have fewer gatekeeping layers and less call volume. The same administrator or office manager often covers multiple locations, and you may reach them more easily at the smaller site. Provider data that maps multiple affiliated locations makes this strategy practical.
Be honest about who you are. Deceptive gatekeeper tactics, pretending to be a patient, claiming a personal relationship, or being vague about your purpose, create short-term wins and long-term problems. Healthcare front desk staff talk to each other. Word gets around. Instead, be direct and respectful: state your name, your company, and that you have information relevant to [specific topic] for [specific person]. If the gatekeeper asks you to send an email instead, take the email address and do it. That email, with a subject line referencing the call, often gets opened.
Building a Repeatable Cold Calling System with Provider Data
Individual call techniques matter; however, what separates productive reps from struggling ones is the system. A repeatable, data-driven cold calling system ensures consistent activity and measurable improvement over time.
Build segmented call lists from provider data. Don't call from a single flat list. Segment by practice size, specialty, geography, installed technology, or any other relevant dimension. Then prioritize: call your highest-fit accounts first each day, when your energy and focus are sharpest. Provider data platforms with filtering capabilities let you build these segments in minutes. Refresh your lists monthly to account for new practices, closures, and provider changes.
Where Do You Get Provider Phone Numbers for Cold Calling?
Four source types cover the market, and they differ mostly in how often the number connects to the person you want.
The NPI Registry is a public identity source and often includes a self-reported practice phone. Treat that number as an observed registry field rather than a direct line. Confirm the practice and channel before a calling campaign, and retain stale or shared numbers as exceptions.
Practice websites and Google Business profiles. More current than registry data for the main line, since practices keep their patient-facing number working. Still a gatekeeper number. Useful for confirming a practice is open and operating at the listed address before you burn a dial.
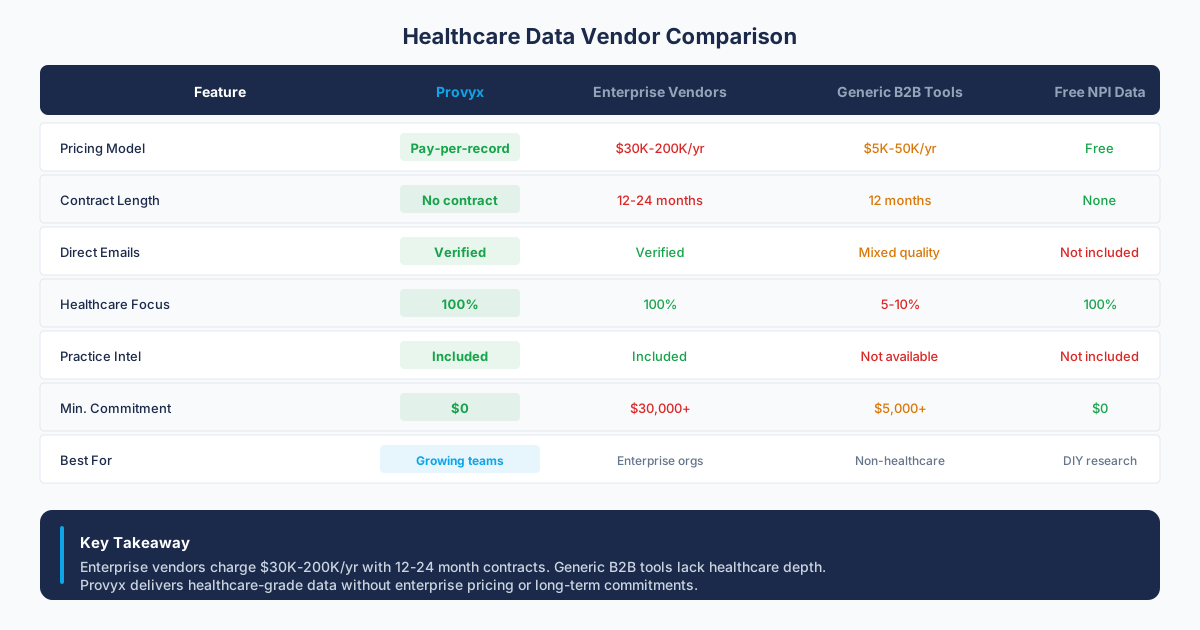
Healthcare-specific provider data vendors. Built from the provider universe outward: NPI-linked records with practice context, decision-maker names, and business phone numbers verified at delivery. This is what Provyx builds. Each list is assembled when ordered, and verified mobile numbers are available as an add-on, billed per number found. For a calling program, the practical difference shows up in the connect rate: a verified list with named contacts turns more of your dials into conversations with the right person.
Frequently Asked Questions
Should I cold call physicians directly or target practice administrators?
It depends on your product and practice size. For clinical products (devices, drugs), physicians are often the initiator of the buying process, so reaching them matters. For operational products (software, services, supplies), the practice administrator or office manager is usually the decision-maker. In larger organizations, targeting the administrator first can be more efficient because they can champion your product internally and connect you with the right clinical contacts.
Is cold calling still effective in healthcare, or should I focus on email and social selling?
Cold calling remains the highest-conversion outbound channel for healthcare sales, particularly for reaching physicians and practice administrators who don't engage heavily on LinkedIn or respond to cold emails. The most effective approach is multi-channel: call first, then follow up with email the same day. Healthcare professionals receive fewer cold calls than their counterparts in technology or financial services, which means a well-executed call still stands out.
Do TCPA and Do Not Call rules apply to B2B calls to medical practices?
The federal Do Not Call Registry covers residential and personal numbers, so calling a practice's business line for a B2B purpose is generally permitted. TCPA restrictions on autodialers and prerecorded messages still apply to any call, and calling a cell phone brings stricter rules, so manual dialing to business lines is the conservative approach. This is general information rather than legal advice; if you run high-volume outbound, have counsel review your process. Source: FCC telemarketing guidance. Source: https://www.fcc.gov/general/telemarketing-and-robocalls.
Where can I find direct phone numbers for practice administrators?
Direct dials for administrators come from commercial provider data vendors rather than public sources. The NPI Registry and practice websites list main office lines only. Healthcare-specific vendors attach the administrator or owner as a named contact with a business phone on the practice record, and some offer verified mobile numbers as an add-on. Whatever the source, test a sample before buying a full list: a batch of 50 dials tells you quickly whether the direct-dial claims hold up. Source: CMS NPPES files.
What should a call-list sample test?
Test whether each number reaches the intended practice or role, record wrong-party and disconnected outcomes, and compare direct and main-line fields separately. Keep the call date with the result.
Sources and References
Related Resources
Get the Provider Data You Need
Tell us what you're looking for. We'll build a custom list matched to your target market.
Trusted by healthcare sales teams, medical device companies, and health IT vendors across the US.