
Definitive Healthcare Alternative for Provider Contact Data
Compare Definitive Healthcare and Provyx against the same use case, fields, evidence standard, and delivery workflow. Review the current Definitive Healthcare product documentation alongside the written Provyx scope before deciding.
Updated September 2026
Definitive Healthcare Product Scope
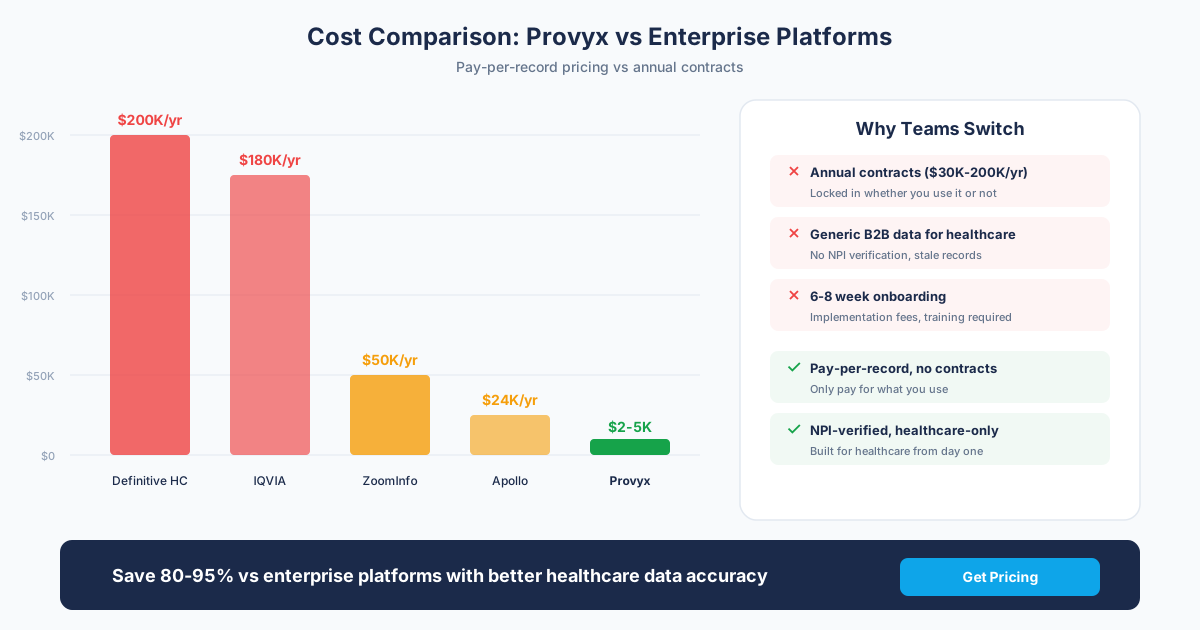
Provider contact records sit inside that platform as one module among many. That bundling is the whole story of its pricing. You cannot buy the contact layer on its own, so a team that needs provider lists ends up licensing claims analytics, hospital intelligence, and dashboards it may never open. Teams searching for a Definitive Healthcare alternative are usually trying to unbundle that purchase, keeping the provider data workflow and dropping the analytics subscription. Our healthcare data vendor comparison maps the full vendor landscape if you want the wider view before reading this side-by-side. Source: Definitive Healthcare product documentation.
Why Teams Look for a Definitive Healthcare Alternative

Definitive Healthcare
Definitive Healthcare built its reputation on deep intelligence about hospitals, health systems, and IDNs. If you're mapping referral networks, analyzing claims data, or tracking hospital capital budgets; this is one of the strongest platforms available. The problems surface when teams buy Definitive for a different job: building provider contact lists for outbound sales and marketing.
Strong on hospitals, weaker on individual providers and small practices. Definitive Healthcare's core data asset is its hospital and health system intelligence: bed counts, technology installations, C-suite contacts, financial performance, and claims volume. When you move down to individual physician contacts and small group practices, the depth drops off. A two-provider family medicine practice in a suburban office park isn't covered with the same richness as a 500-bed academic medical center. If your sales motion targets those small and mid-size practices, which represent a large segment of the healthcare provider workforce, the data you're using doesn't justify the price you're paying.
A static database that ages between syncs. Definitive's data refreshes on their internal schedule. Whatever providers, addresses, and contacts are in the platform today is the snapshot every customer sees, regardless of when it was last updated. For a hospital strategy team that's fine, because the underlying entities don't change weekly. For a sales team trying to reach individual providers and small practices, where staff turn over, addresses change, and contact info degrades constantly, a static snapshot is the wrong shape of data. Each Provyx list is built when your order comes in, pulled from the current NPI registry and current state licensing boards, then triangulated across multiple sources before delivery. Source: CMS NPPES files.
Export and download limitations. Even with a paid subscription, Definitive Healthcare limits how many records you can export per month or per query. For sales teams that need to pull large lists regularly and push them into a CRM or outreach tool, these caps create bottlenecks. You may end up rationing your exports or submitting requests to the platform team for bulk downloads, adding delays to what should be a straightforward workflow. Source: https://www.definitivehc.com/data-products/claims.
Definitive Healthcare is a strong product for the use cases it was designed for. The mismatch happens when teams buy it as a provider contact database, because that's not where its strength is concentrated.
✓ Reasons to Switch
- Get NPI-verified individual provider contacts
- Simpler workflow: no analytics platform learning curve
- Practice-level data optimized for outreach rather than analysis
✗ Reasons to Stay
- You actively use claims data and procedure volume analytics
- You need hospital technology installation tracking
- Your strategy depends on referral network mapping
- You target health system executives (C-suite contacts)
Definitive Healthcare and Provyx Evaluation Inputs
The pricing gap between Definitive Healthcare and Provyx reflects different product philosophies. Definitive Healthcare bundles provider contacts with analytics, claims data, and hospital intelligence into a single platform subscription. Provyx builds and verifies provider contact records as a standalone project with project-based pricing. If your team uses the full analytics suite, the bundled approach makes sense. If your team mainly exports provider lists for outbound, you are paying for capabilities you do not use. Source: Definitive Healthcare product documentation.
| Definitive Healthcare | Provyx | |
|---|---|---|
| Entry price | Confirm in current vendor documentation or a written quote | Verify the measured value and observation date before use. |
| Full platform | Confirm in current vendor documentation or a written quote | Per validated contact |
| CRM integration | Confirm in current vendor documentation or a written quote | CSV or Excel |
| Contract | Confirm in current vendor documentation or a written quote | |
| Per-seat licensing | Yes (per user) | No per-seat fees |
| Data export | Platform-dependent, monthly caps | Full export included |
What Healthcare Teams Need from a Provider Data Source
Teams doing outbound sales and marketing to healthcare providers have a specific set of data requirements. These requirements look different from what a market access team or a hospital strategy group needs.
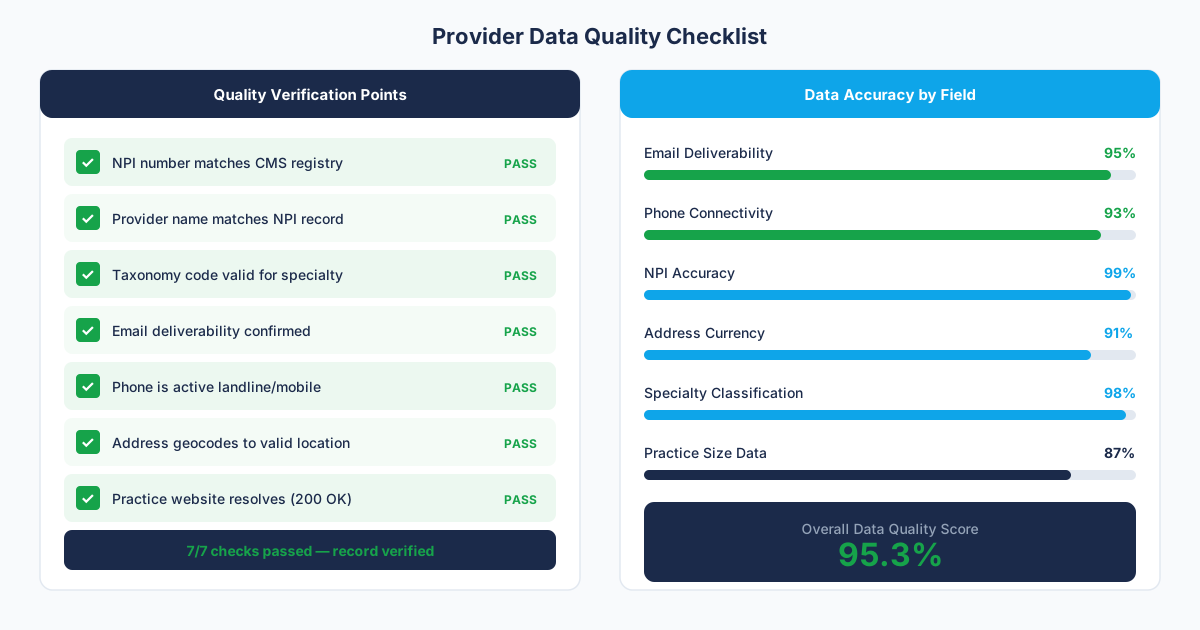
NPI verification on every record. The National Provider Identifier is the standard unique identifier for healthcare providers in the United States. When your data includes verified NPIs, you can confirm that a contact is a currently credentialed provider rather than a retired physician or a mismatched record. Outbound campaigns built on unverified data waste rep time and damage your brand when calls go to wrong numbers or outdated contacts.
Practice-level contact information. Sales reps don't call hospital systems at their corporate headquarters to reach a physician. They call the practice where the doctor sees patients. Practice name, direct phone number, fax number, street address, and website are the fields that drive outbound activity. A platform optimized for hospital intelligence may not prioritize these practice-level details.
Specialty-aware geographic segmentation. Healthcare is local. A sales territory might cover a metro area or a cluster of ZIP codes. The ability to filter by specialty classifications and geographic boundary at the same time is how teams build territory-ready prospect lists. Broad analytics platforms may offer geographic filtering; however, combining it with granular specialty classifications at the individual provider level is where many fall short.
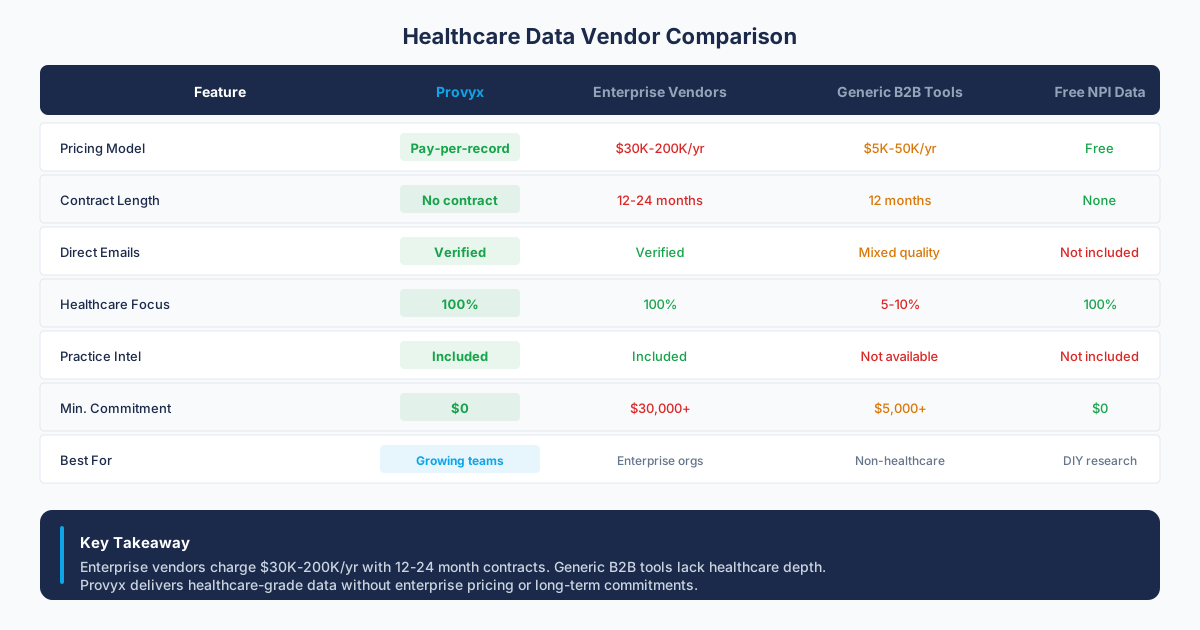
Definitive Healthcare vs. Provyx: Quick Comparison
| Factor | Definitive Healthcare | Provyx |
|---|---|---|
| Starting Price | Confirm in current vendor documentation or a written quote | Verify the measured value and observation date before use. |
| Contract Terms | Confirm in current vendor documentation or a written quote | |
| Healthcare Specialties | Claims-based categories Broad | specialty and subspecialty coverage Granular |
| NPI Verification | Facility-focused Partial | Every record NPI-Verified |
| specialty classifications | Secondary to claims Limited | Primary classification On All Records |
| Practice Data | Hospitals strong, small practices weak Mixed | All sizes covered Full Detail |
| Data Delivery | Confirm in current vendor documentation or a written quote | CSV or Excel Included |
| Best For | Hospital/system analytics and strategy teams | Teams running outbound to individual providers |
How Provyx Works as a Definitive Healthcare Alternative
Data Sourcing
Provyx builds its provider records from three source categories:
- Public NPI registries: The NPPES database maintained by CMS provides the foundation: NPI numbers, specialty classifications, enumeration dates, provider names, and practice addresses as reported for Medicare and Medicaid billing. This is the same data that Definitive Healthcare uses as one of its inputs; however, Provyx makes it the primary layer rather than one of many.
- Business listings and public records: State licensing boards, secretary of state business filings, public web directories, and healthcare-specific directories add practice phone numbers, websites, fax numbers, and ownership details. These sources fill the gaps that the NPI registry doesn't cover, particularly for practice operations data.
- Commercial databases: Third-party data providers contribute technology detection, LinkedIn profile matching, estimated revenue ranges, and staff size indicators. This layer adds firmographic and technographic depth to the base contact record.
NPI Verification
Every individual provider record in Provyx has been matched against the current NPPES data. The verification checks that the NPI is active and not deactivated, the provider's name matches the NPI record, and the specialty classification reflects the provider's current reported specialty. Definitive Healthcare includes NPI data; however, its verification emphasis is on facility and system identifiers rather than individual provider records. Provyx treats individual provider NPI verification as a first-class requirement because that's what outbound sales teams depend on. Source: https://www.definitivehc.com/data-products/claims.
What You Get in Each Record
A Provyx provider record includes:
- Provider full name
- NPI number (Type 1 for individuals, Type 2 for organizations) Source: CMS NPPES files.
- Primary and secondary specialty classifications with human-readable specialty labels
- Practice name and DBA name
- Practice mailing address and location address
- Direct phone number and fax number
- Practice website URL
- Practice owner name (from public records where available)
- LinkedIn profile URL (where matched with high confidence)
- Enumeration date
Delivery Formats
Provyx delivers data as:
- CSV files: for CRM import or custom processing.
- Excel workbooks: with formatted columns and headers, ready for reps.
There's no mandatory platform login to access your data. You don't need to learn a new interface or schedule a training session. You define your filters, receive your file, and put it to work.
Provyx Scope Boundaries
Provyx covers a narrower provider-contact workflow than Definitive Healthcare's analytics platform.
Provyx doesn't map health system org charts, track hospital M&A activity, or provide capital budget intelligence. If your team's workflow depends on understanding health system hierarchies and affiliate relationships, Provyx isn't the right tool.
Provyx doesn't include an integrated sales engagement layer. There's no built-in email sequencing, no phone dialer, and no intent data scoring. This is a data source that feeds into whatever outreach tools your team already runs.
Provyx also doesn't cover payer data, ACO network analysis, or facility accreditation details. Those are specialized data sets that Definitive Healthcare includes for strategy and market access teams. If your team depends on those data points, removing Definitive Healthcare entirely would leave a gap.
What Provyx does is deliver verified provider contact records. If that's the specific job you're hiring a data source to do, it does it well and it does it at a lower cost than platforms that bundle it with features you aren't using. Source: current Provyx scope and pricing.
Who Switches from Definitive Healthcare to Provyx
The teams that switch share a common pattern: they bought Definitive Healthcare for contact data and realized they were paying for an analytics platform they didn't need.
Medical Device Sales Teams
Healthcare Marketing Agencies
Health IT Companies Selling to Practices
Pharma Commercial Teams with Regional Focus
How to Switch from Definitive Healthcare to Provyx
If you're considering a move, here's a practical evaluation path that doesn't require canceling anything upfront.
Step 3: Buy a single list. Don't negotiate a migration plan until you've validated the data in production. Purchase one list for one territory or specialty segment. Import it into your CRM and let your team work it for two to four weeks. Collect concrete feedback on data quality and coverage.
Our Recommendation
The Bottom Line
If you're using Definitive Healthcare mainly to pull provider contact lists, you're paying enterprise analytics pricing for a basic data export workflow. Source: Definitive Healthcare product documentation.
- Keep Definitive: If you use claims analytics, referral mapping, or hospital technology data regularly.
- Switch to Provyx: If your main workflow is building provider contact lists for sales and marketing.
- Use both: Definitive for strategic analysis, Provyx for tactical outreach list building.
Questions to Ask Before Signing
- What Definitive features do you use weekly?: If it's mainly contact list exports, you're overpaying.
- Does your team fully use the analytics platform?: Enterprise analytics require dedicated analyst resources.
What belongs in the alternatives definitive healthcare alternative evaluation record?
The alternatives definitive healthcare alternative evaluation record should begin with the job the data will perform. Name the audience, destination workflow, fields used by that workflow, and the source that resolves conflicting values. Keep provider identity separate from practice identity, and keep both separate from the parent organization. That structure lets the review team see whether a failure belongs to the person, the location, the relationship, or the contact channel.
Define the acceptance rule before reviewing a sample
Keep disagreements visible
Test the operating handoff
Preserve a baseline for the next review
Replace a workflow, not a product name
Begin with the analyses, datasets, exports, integrations, and reports the team uses today. Separate institutional intelligence from provider contact delivery. The replacement set may be one tool, several tools, or a narrower service paired with an existing analytics workflow.
Build a sample from real hospitals, physician groups, independent practices, clinicians, and ambiguous affiliations. Apply one definition for each field and preserve the source behind accepted and unresolved values. This shows which candidate handles the hard relationships rather than only the obvious records.
Make the operating differences visible
Rehearse exports and imports in a disposable workspace. Inspect identifiers, field mapping, record limits, duplicates, update behavior, permissions, and correction handling. Include the analyst work needed to turn the output into an approved campaign or analysis file.
Document the final boundary. State which system owns institutional analytics, which one owns provider identity and contact fields, and where exceptions go. Save the sample, mapping, and rejected rows so future reviewers can reproduce the decision.
Map each retained capability to an owner
Separate hospital and health-system intelligence, claims-derived analysis, referral relationships, market sizing, provider identity, practice affiliations, contact research, and campaign delivery. For each capability, name the current users, receiving systems, critical fields, and decision it supports. This prevents a broad replacement label from hiding several distinct jobs.
Mark capabilities that can be retired rather than automatically recreating them. Review actual use, downstream dependencies, and the consequence of losing the output. An unused dashboard and a field driving account prioritization should not receive equal weight simply because both appear in the present contract.
Design a sample around the hard relationships
Include health systems with regional brands, acquired practices, independent groups, individual clinicians, several care sites, and conflicting affiliations. Ask each candidate workflow to represent the entities and relationships without flattening them into one company record. Preserve missing and unresolved outcomes.
Score institutional analysis separately from provider outreach readiness. Define acceptable evidence, observation dates, and review rules for each field. When a derived metric is important, record its population and method. When a contact channel is important, resolve the person and practice before accepting it.
Rehearse the replacement operating model
Move the frozen sample through exports, transformations, imports, permissions, deduplication, and correction handling. Include analyst work performed outside the tool. If several products share the job, document their identifiers, update order, and conflict rules.
The final record should name the owner and system of record for each retained capability, plus the exception queue and review cadence. Keep the tested input, accepted mappings, rejected rows, and user notes. That evidence lets procurement and operations revisit the choice without relying on a sales demonstration.
Frequently Asked Questions
Which Definitive Healthcare capabilities belong in the inventory?
List the datasets, analytics, saved views, exports, integrations, permissions, and downstream workflows the team uses. A contact-data need and an analytics need should be evaluated separately. Source: https://www.definitivehc.com/data-products/claims.
How should a replacement sample be designed?
Select representative hospitals, practices, clinicians, and edge cases from the real workflow. Apply the same field definitions and source dates to each candidate output. Source: https://www.definitivehc.com/data-products/claims.
What should an export rehearsal test?
Test field mapping, record limits, duplicates, rejected rows, update behavior, and the path for corrections. Save the sample and mapping so operations can reproduce the handoff. Source: https://www.definitivehc.com/data-products/claims.
When does a narrower provider-contact workflow fit?
A narrower workflow fits when the operating job is a defined outreach list rather than institutional analysis. Document the excluded analytics and confirm that another system owns them. Source: https://www.definitivehc.com/data-products/claims.
Who should sign off on the replacement workflow?
Include the analysts who use institutional intelligence, the operators who prepare outreach data, the CRM owner, and the people who resolve exceptions. Each reviewer should approve the part they will operate.
Ready to See How Provyx Compares to Definitive Healthcare?
Get provider data for your specialty and geography. Compare it side-by-side with what you're getting from Definitive Healthcare today.
Trusted by healthcare sales teams, medical device companies, and health IT vendors across the US.
Separate migration risk from feature preference
Identify reports, segments, territories, and integrations that would break if a field changes name, meaning, or owner. Test those dependencies with the frozen sample before evaluating convenience or interface preference. A capability can look replaceable while its downstream definitions remain deeply embedded.
For records shared between institutional analysis and outreach, choose a stable join key and keep relationship history. A clinician's current care site, group affiliation, and parent system can change independently. The replacement workflow should preserve those distinctions and expose conflicts to reviewers.
Define acceptance by operating role
Analysts should approve the fields used for research and prioritization. Data operations should approve mappings, update behavior, and exception handling. Sales operations should approve account ownership and usable contact paths. Security and procurement should review the proposed access model and written terms within their remit.
Consolidate those decisions into one test record without averaging away a failed critical workflow. If a necessary capability remains unresolved, name the temporary owner and the evidence needed to close it. This gives the migration a verifiable exit condition.